Hair transplant gone wrong: the three categories of failure, real clinical causes and what can actually be corrected.
A hair transplant gone wrong is not a minor inconvenience. The donor zone is a finite biological resource. A depleted or damaged donor area cannot be restored. An unnatural hairline built from the wrong angles cannot be simply "undone." The consequences of a failed or poorly executed hair transplant are permanent — and understanding what causes them is the most important thing any prospective patient can learn.
The Three Categories of Hair Transplant Failure
Hair transplant failures are not random events. They fall into three distinct categories with distinct causes. Understanding which category applies to a specific bad outcome helps patients understand both what went wrong and what correction options exist.
Category 1: Aesthetic Failure — The Grafts Grew, But It Looks Wrong
Aesthetic failure is the most common type of hair transplant gone wrong. The follicles survived and grew — but the result looks artificial, unnatural, or disconnected from the patient's face. Specific presentations:
- Hairline too low: Positioned below what is age-appropriate, creating a bizarre appearance particularly as the face ages
- Hairline too straight: Linear, geometric hairline with no soft irregularity at the leading edge — the most recognisable "hair transplant look"
- Plug appearance: Dense grafts placed at uniform spacing with visible skin gaps between — typically from older FUT techniques or poorly executed FUE
- Wrong angle: Grafts implanted at 90° to the scalp surface instead of 30–45°, producing hair that stands outward rather than lying flat
- Island effect: Transplanted hair surrounded by continued native recession, creating an isolated zone of density that looks incongruous
Category 2: Graft Survival Failure — The Result Is Sparse
Survival failure occurs when a significant proportion of transplanted grafts do not produce growth. The patient receives surgery, waits 12 months, and the result shows significantly less density than was planned. Causes are primarily surgical quality failures: high transection during extraction, excessive out-of-body time, poor graft handling, or inadequate irrigation during implantation.
For anyone considering a hair transplant procedure, understanding graft survival rates and asking specifically about them is an essential pre-booking step.
Category 3: Donor Zone Damage — The Irreversible Harm
Donor zone damage is the most serious category because it is the least correctable. Over-harvesting the donor zone produces visible thinning or patchy appearance at the back and sides of the scalp. The extracted follicles cannot be restored. In severe cases, the donor zone is depleted to the point where future corrective sessions are impossible — leaving the patient permanently unable to address the original hair loss.
Clinical Causes — What Actually Goes Wrong
Technician-Led Surgery: The Root Cause of Most Failures
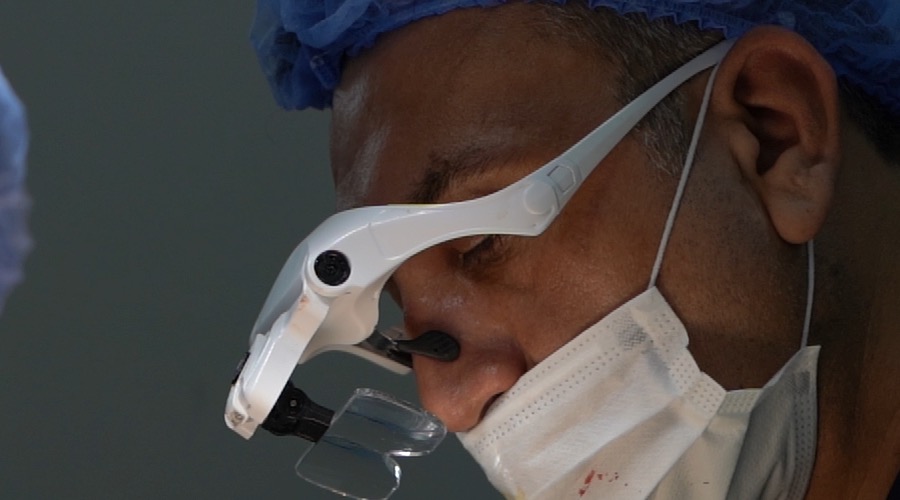
The single most common cause of hair transplant failures across all three categories is delegation of surgery to unlicensed technicians. In high-volume Istanbul clinics, extraction and implantation are routinely performed by staff who are not physicians — trained for weeks or months in a mechanical procedure they perform dozens of times per day, without the anatomical training, pattern recognition or aesthetic judgment that comes from medical education and years of surgical practice.
The consequences of technician-led surgery:
- Higher transection rates: Technicians lack the anatomical knowledge to read follicle angle variations across the donor zone, producing higher rates of punch-through follicle damage
- Aesthetic judgment absent: Channel creation and implantation angles are performed mechanically, without the artistic judgment that produces natural results
- Hairline design delegated: In some clinics, the hairline is designed by administrative or "patient coordinator" staff, not the operating physician
- No complication recognition: Technicians cannot identify complications during surgery or adapt technique in response to unusual anatomy
Over-Graft Promises: The Mathematics of Over-Harvesting
The safe extraction ceiling — the maximum number of grafts that can be taken from a donor zone without producing visible thinning — is typically 5,000–7,000 over a lifetime, depending on donor density and scalp size. Single-session safe extraction is generally 3,500–4,500 grafts while maintaining donor zone integrity.
Clinics that promise 6,000–8,000 grafts routinely exceed this limit. The mathematics are unforgiving: extracting 60 grafts/cm² from a zone with native density of 80 FU/cm² removes 75% of the follicles — leaving visible thinning that is permanent. The patient's frontal result may look acceptable while their donor zone reveals exactly what was sacrificed to achieve it.
Multiple Simultaneous Patients: The Time Pressure Effect
Time pressure produces measurable quality degradation in hair transplant surgery. When a clinic is processing 6–8 patients simultaneously, grafts that have been extracted wait longer before being implanted as shared technical staff move between operating theatres. Out-of-body time extends. Graft viability decreases. The extraction pace is accelerated to meet scheduling requirements, increasing transection rates. None of this is visible to the patient during surgery. All of it appears in the 12-month result.
Inadequate Post-Operative Support: Preventable Graft Loss
A significant number of graft survival failures are not caused by the surgery itself but by inadequate post-operative guidance. Patients who do not understand that grafts can be dislodged in Days 1–10, who sleep on the recipient zone, who return to physical activity too quickly, or who do not follow the washing protocol correctly can lose substantial proportions of their grafts to preventable mechanical disruption.
| Cause of failure | Category affected | Preventability |
|---|---|---|
| Technician-led surgery | All three categories | 100% — by surgeon selection |
| Over-extraction promises | Donor damage, sparse result | 100% — by surgeon selection |
| Multiple simultaneous patients | Graft survival, aesthetic | 100% — by clinic model selection |
| Poor graft storage | Graft survival | 100% — by surgeon selection |
| Post-operative non-compliance | Graft survival | High — by patient education |
Corrective Surgery: What Can and Cannot Be Fixed
The correction possibilities for hair transplant gone wrong vary significantly by failure type. Understanding correction limitations is as important as understanding the original failures.
Aesthetic failure (hairline position): A hairline that is too low can be partially corrected by electrolysis or laser removal of the most anterior grafts, followed by potential redistribution. Full restoration to a natural position requires removing and redistributing significant numbers of grafts — technically demanding, multiple sessions, and never fully reversible. Prevention is orders of magnitude easier than correction.
Aesthetic failure (unnatural angles): Grafts that grew at the wrong angle produce hair that cannot be styled to lie naturally. Correction requires removal of the offending grafts and replacement — if donor supply permits. If donor supply was already depleted, options are severely limited.
Sparse result from survival failure: If donor supply is intact, a supplementary session can increase density. If the original procedure used maximum donor extraction, the correction options are limited.
Donor zone damage: The most difficult to correct. Body hair transplant (chest, beard) can partially supplement the depleted donor zone but provides grafts of lower quality than scalp donor. The original density cannot be fully restored. This is the most severe and least correctable outcome in hair restoration.
For information on Dr. Arslan's corrective surgery capabilities and philosophy, visit Hairmedico about us.
Prevention: The Surgeon Selection Framework
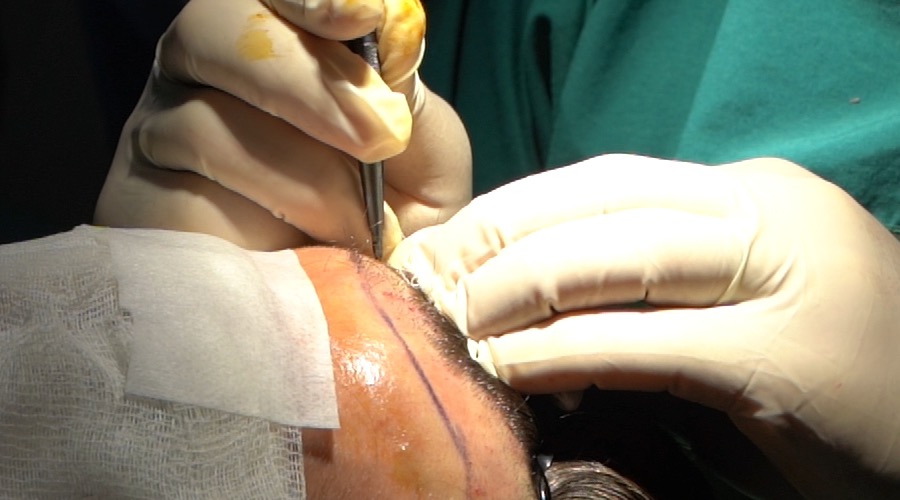
Every category of hair transplant failure is preventable with the right surgeon selection. The five questions that eliminate the majority of failure risk:
- "Does the named surgeon personally perform extraction and implantation?" — The surgeon must confirm personal performance. "Supervises" or "oversees" is not an acceptable answer.
- "How many patients does the clinic treat per surgical day?" — One is the answer at quality clinics. More than two is a significant concern.
- "What is your documented graft survival rate?" — Should be 90%+. Should be backed by measurement, not claim.
- "Can I verify your credentials independently?" — FUE Europe andship should be independently verifiable.
- "What is your post-operative protocol and what does the follow-up include?" — 12-month surgeon-accessible follow-up should be standard and included.
For transparent pricing of Hairmedico's surgeon-led procedures, visit hairmedico.com/price.
