
01 · Bespoke Assessment
Free photo review
Submit three photographs. Dr. Arslan reviews every case personally within 24 hours and tells you plainly whether surgery is the right next step.
Surgeon-led hair restoration clinic in Levent, Istanbul since 2005.
Explore all →Send 3–5 photographs. Personal response within 24 hours — no intermediaries.
Request Now →Selected for your specific hair loss pattern and aesthetic goals.
FUE vs DHI →FUE, DHI or Algorithmic FUE™ — Dr. Arslan recommends based on your photographs and Norwood stage.
Get Assessment → Try Graft Calculator →FUE Europe member. Ministry of Health accredited clinic. Levent, Istanbul — 60–80% less than UK or US.
View Package →FUE Europe member. Ministry of Health accredited. 17+ years. 3,000+ personal procedures. One patient per day.
Full Profile →One patient a day, every package surgeon-led. Every result personally accountable.
Read Philosophy →No hidden costs. Hotel, transfers, surgery and aftercare in one price.
View Pricing →Silver · Gold · VIP — 5-star hotel · Airport transfers · PRP included
View Pricing → Graft Calculator →Every case personally overseen by Dr. Arslan Musbeh, from consultation to results.
Full Gallery →Not every case needs a transplant. Medical treatments, therapies and specialist options.
Overview →Guides, tools and expert content — written by Dr. Arslan Musbeh.
All Articles →Hairmedico is a boutique hair restoration clinic founded and medically directed by Dr. Arslan Musbeh, a hair transplant surgeon with more than 17 years of experience. Every treatment plan is created individually according to the patient’s hair loss pattern, donor capacity and long-term needs.
The Process
From your first photographs to a full result at 12 months, with Dr. Arslan Musbeh involved at every stage.
01 · Bespoke Assessment
Submit three photographs. Dr. Arslan reviews every case personally within 24 hours and tells you plainly whether surgery is the right next step.
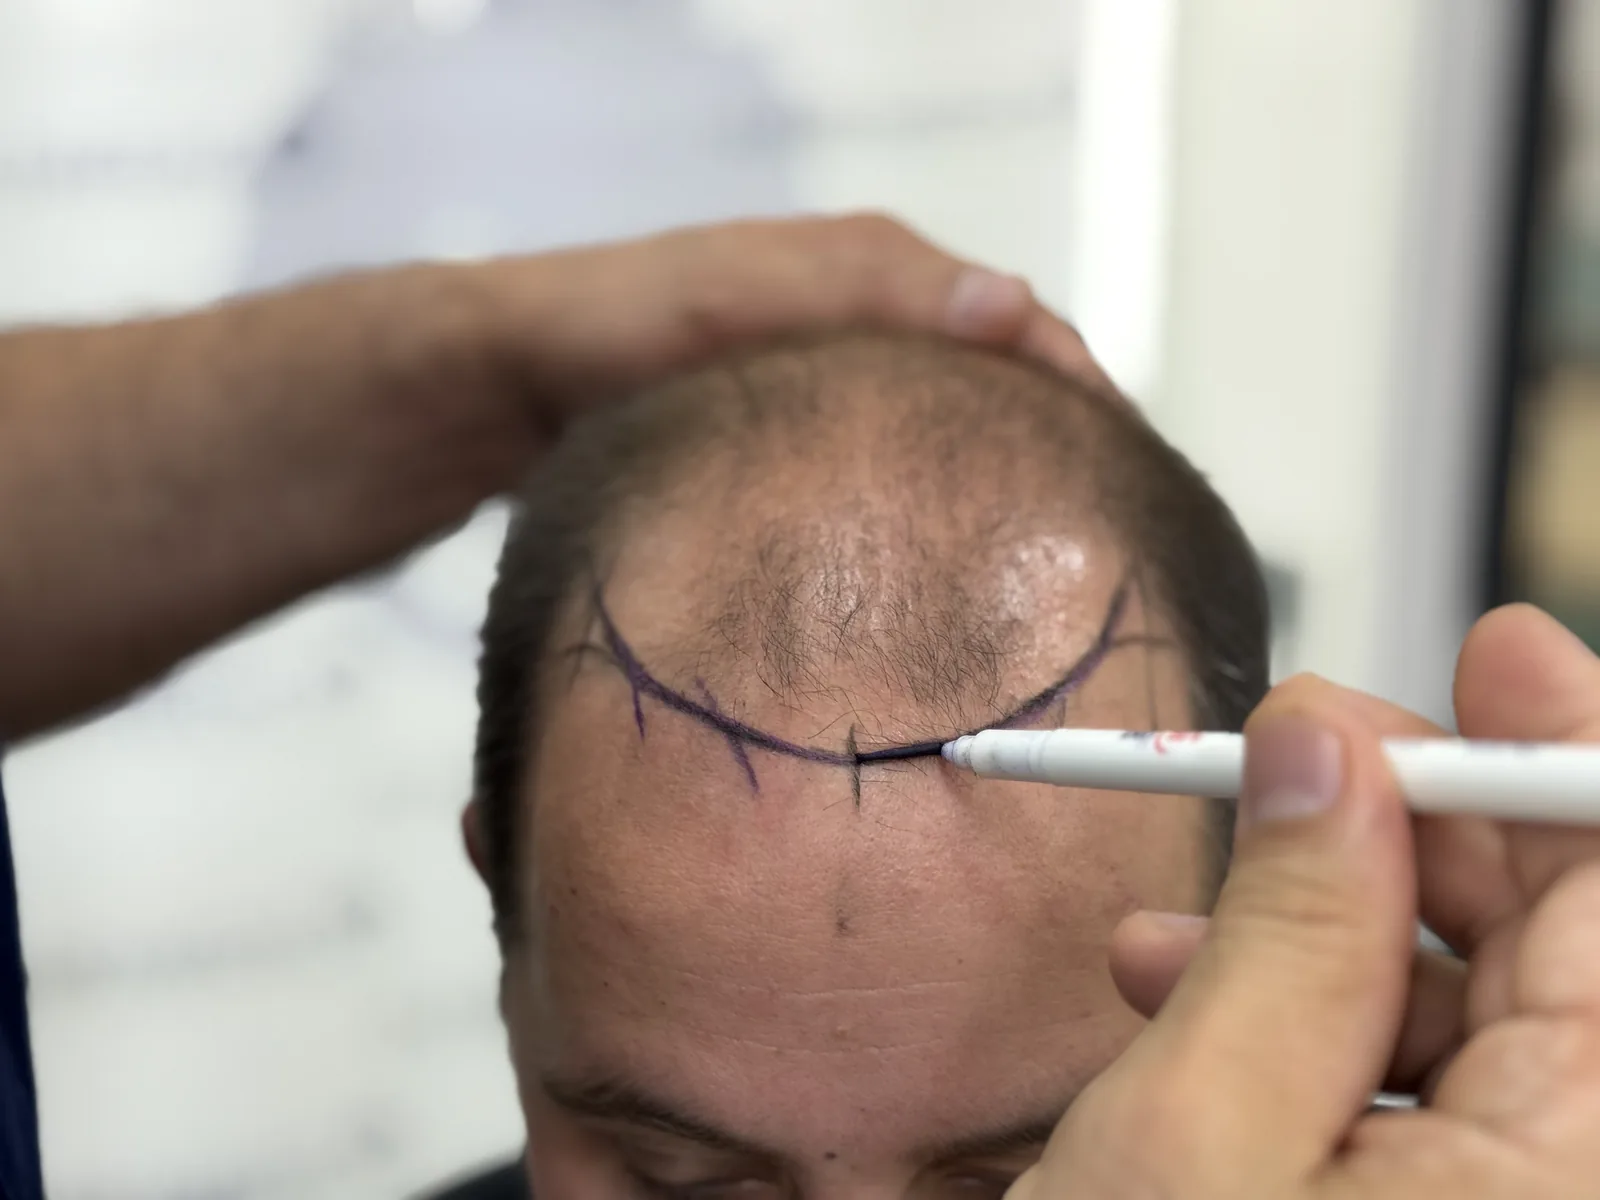
02 · Technique & Plan
FUE, DHI or Algorithmic FUE™ is confirmed by the surgeon directly, with a graft estimate and a fixed, all-inclusive price.

03 · Arrival Istanbul
A VIP transfer meets you at the airport and takes you to your 5-star hotel, followed by a pre-op consultation day at the Levent clinic.
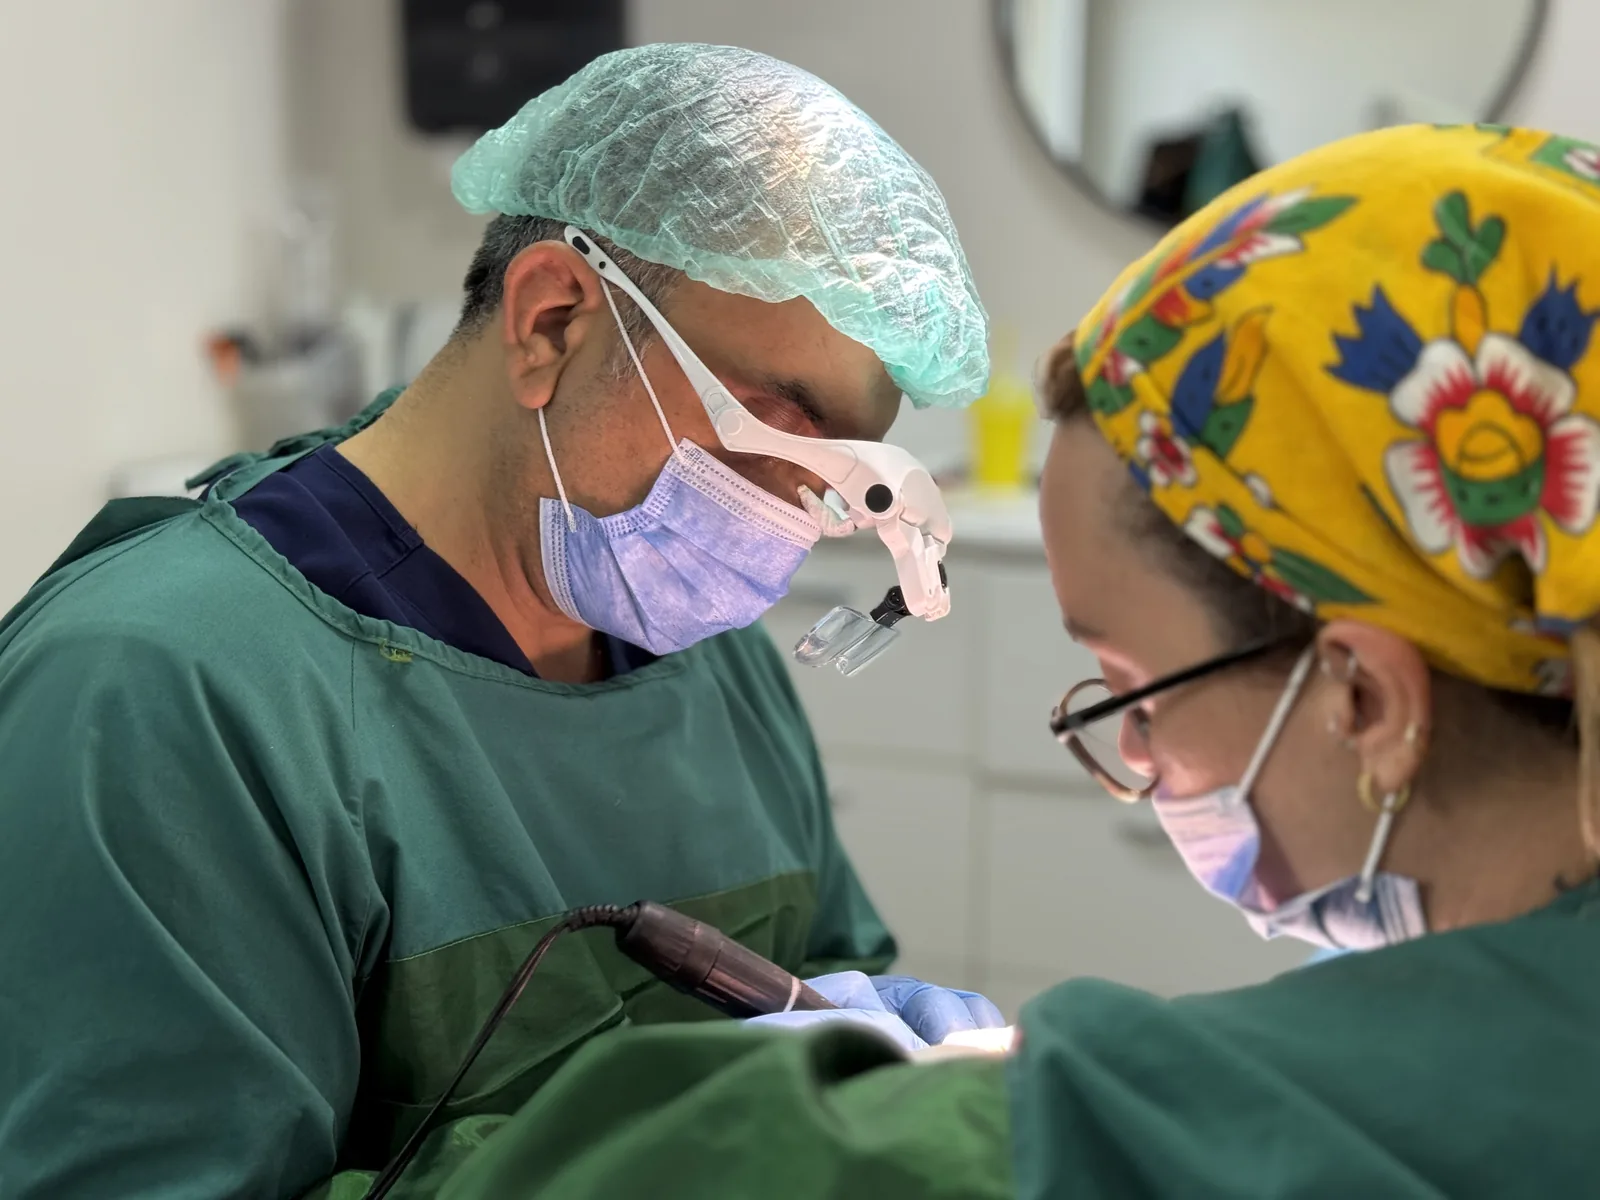
04 · Surgery Day
Dr. Arslan personally leads every package, performing the channel-opening incision himself in Gold and VIP. You are the only patient in the clinic that day.
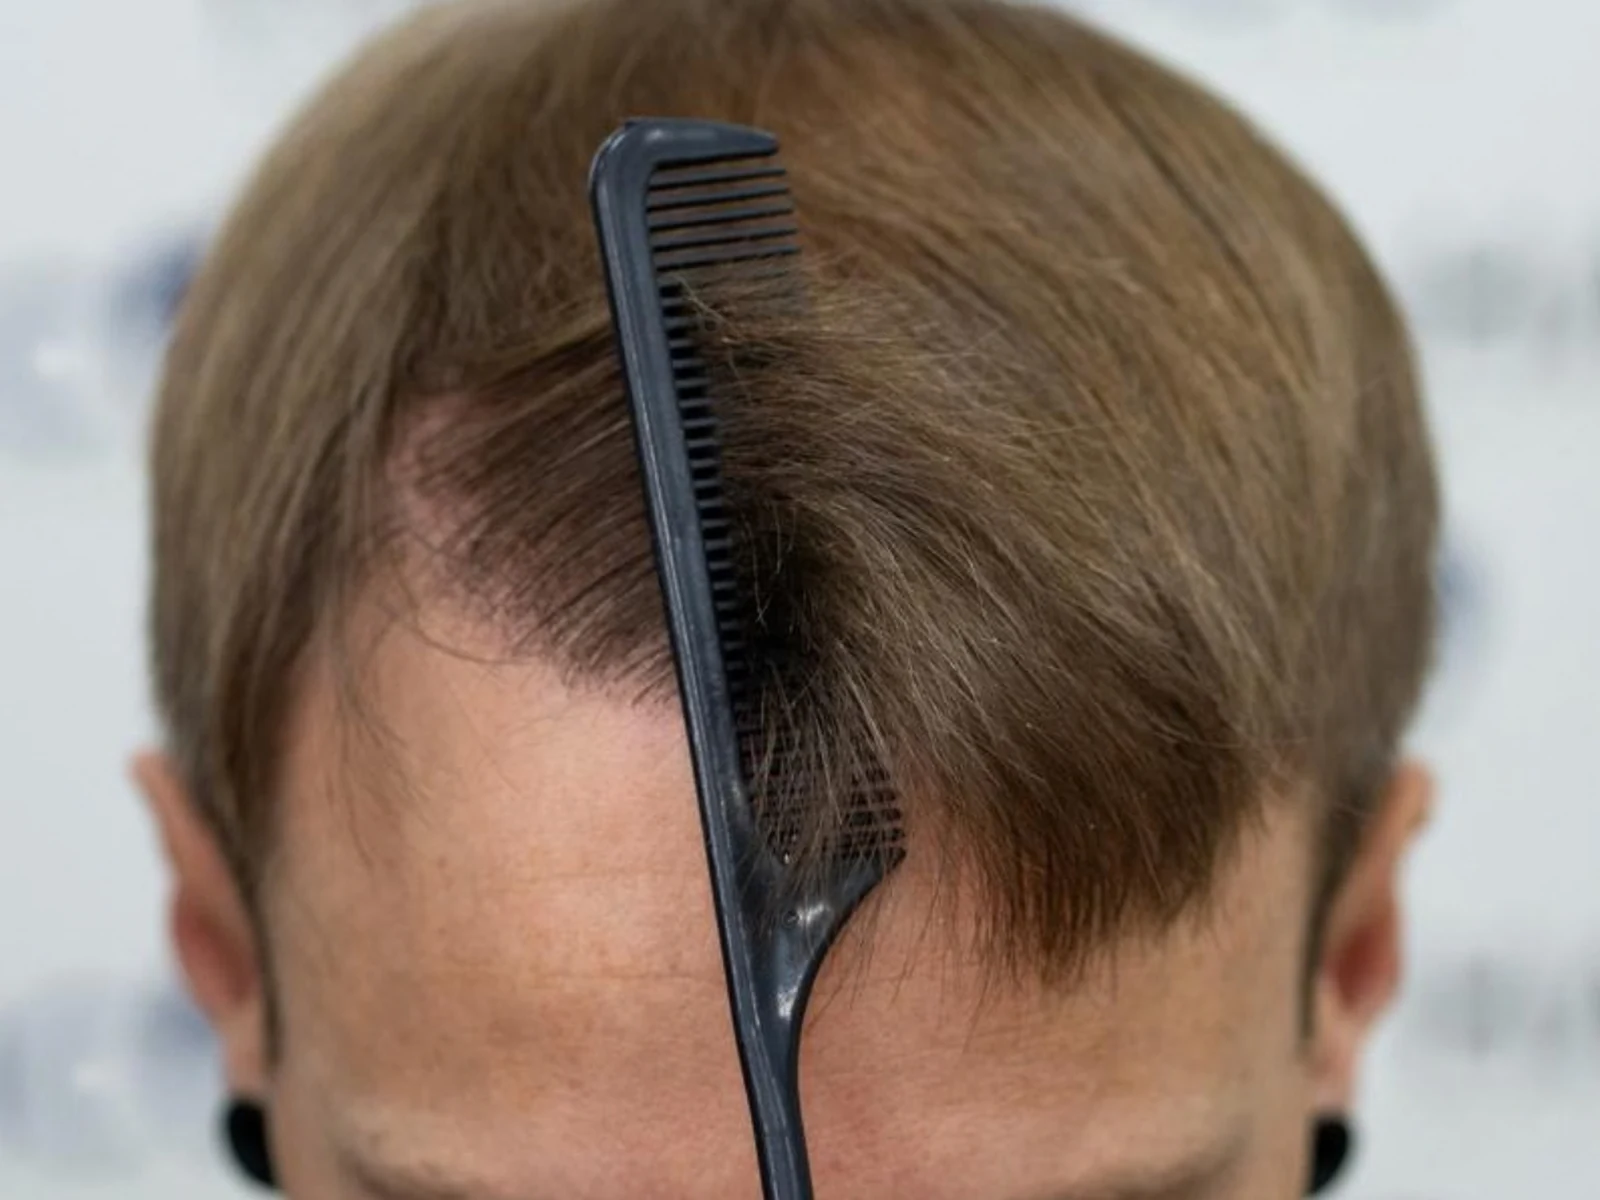
05 · Results at 12 Months
Full result visible at around 12 months. Our team supports you through 12 months of follow-up, including the first wash at the clinic.
Why Hairmedico
Hair restoration is a surgical discipline before it is an aesthetic one. Hairmedico is structured around that principle: fewer procedures per day, individualised planning, and an explicit answer to the question most clinics avoid — who actually performs your surgery.
More than 17 years of surgical experience
A single, consistent surgical philosophy applied across more than a decade and a half of hair restoration practice.
Personalised hairline and donor-area planning
Design is derived from facial proportion, hair calibre, donor capacity and projected future loss — not from a template.
Limited daily surgical schedule
Case volume is capped so that surgical attention, sterility standards and graft handling time are never compressed.
Sapphire FUE, FUE and DHI options
Technique is selected to fit the patient's anatomy and treatment area, rather than the clinic's preferred workflow.
Dedicated protocols for Afro-textured hair and women
Curved follicular anatomy and female pattern loss require distinct extraction, angulation and density strategies.
Multilingual international patient support
Clinical communication in English, French, Turkish, Russian, Kurdish and Arabic — without an intermediary agency.
Long-term postoperative follow-up
Structured review at defined intervals through the full growth cycle, not a single discharge conversation.
Transparent surgical involvement
Each package states in writing which stages are performed by the surgeon and which by the medical team.

Surgical involvement
In many clinics, this question is answered vaguely or not at all. Hairmedico publishes it as a specification. Read the table left to right: each row is a surgical stage, each column is a package, and every cell states who holds the instrument.
| Surgical stage | Silver | Gold | VIP |
|---|---|---|---|
| Medical assessment & diagnosisPattern, donor capacity, calibre, expectations | Surgeon | Surgeon | Surgeon |
| Surgical plan & graft allocationZone-by-zone distribution and donor budget | Surgeon | Surgeon | Surgeon |
| Hairline designPosition, shape, irregularity, age-appropriateness | Surgeon | Surgeon | Surgeon |
| Graft extractionPunch selection, depth, donor preservation | Surgeon | Surgeon | Surgeon |
| Channel creation (recipient sites)Angle, direction, depth, density | Surgeon | Surgeon | Surgeon |
| Graft sorting & preservationDissection control, out-of-body time | Medical team | Medical team | Medical team |
| Graft placementImplantation into prepared sites | Medical team | Medical team | Surgeon |
| Intraoperative supervisionContinuous surgical oversight | Surgeon | Surgeon | Surgeon |
| Postoperative reviewFollow-up through the growth cycle | Surgeon | Surgeon | Surgeon |
Silver
Surgeon-planned
The surgical plan for this package is designed personally by Dr Arslan Musbeh, as in every package. Hairmedico's trained medical team places the grafts according to the surgical plan he designed.
From€2,600
Gold
Surgeon-designed
As with every package, Dr Arslan Musbeh personally performs the consultation and channel-opening incision — the stage that most determines how natural the result reads. The medical team places the grafts following his surgical plan.
From€2,600
VIP
Surgeon-performed
Dr Arslan Musbeh personally performs every stage — graft extraction, channel creation, and graft placement — with no delegation to the medical team. The daily schedule is limited to a single case, so that pacing is governed by the surgery rather than the timetable.
From€2,600
The appropriate package and technique are determined following medical assessment, donor-area analysis and discussion of the patient's expectations. A package is a level of surgical involvement — it is not a discount tier, and it does not change the diagnostic standard applied to your case.
Techniques
No technique is universally best for every patient. The appropriate method depends on the treatment area, existing hair, graft requirement, hair characteristics and surgical plan — and in many cases, two methods are combined within a single procedure.
Follicular units are extracted individually from the donor area with a micro-punch, then placed into recipient channels created by the surgeon. It remains the reference technique for large sessions and for cases where extraction strategy matters more than placement instrumentation.
Typically considered for: broad coverage across frontal and mid-scalp zones, high graft counts, cases requiring careful donor distribution.
A variant of FUE in which recipient channels are created with sapphire-tipped blades. The blade geometry allows narrow, controlled incisions, which supports tighter placement and precise control of angle and direction along the hairline.
Typically considered for: dense frontal reconstruction, refined hairline transition zones, patients with fine hair calibre.
Grafts are loaded into an implanter pen, which creates the site and places the follicle in a single motion. This reduces out-of-body time for the graft and is useful where the surrounding native hair must be preserved.
Typically considered for: unshaven or partial-shave procedures, density work between existing hair, defined smaller zones.
A clinic that performs one technique will recommend that technique. Hairmedico's sequence is the reverse: assessment first, plan second, technique third.
The variables that decide the method are measurable — hair calibre and curl, follicular grouping in the donor area, laxity, scalp thickness, the surface area to be covered, the density of any surviving native hair in the recipient zone, and the amount of donor that must be reserved for future sessions.
When those variables are documented before the method is chosen, technique becomes a clinical decision. When they are not, it becomes a marketing one.

Design & donor strategy
A successful hair transplant is not defined only by the number of grafts. Hairline position, follicle direction, graft distribution, donor preservation and future hair loss must be evaluated together.
A hairline placed too low or too straight will look acceptable at thirty and incongruent at fifty. Because androgenetic alopecia is progressive, the design must remain proportionate as the surrounding native hair continues to change.
Hairmedico prioritises natural, age-appropriate hairline design and responsible donor management rather than pursuing the highest possible graft number. Design considers facial proportion, forehead height and shape, the frontotemporal recession angle, the deliberate irregularity of the transition zone, and the single-hair grafts that make the leading edge read as natural rather than drawn.
The donor area is a finite resource. Every graft taken today is a graft unavailable in ten years.
Large graft numbers are easy to sell and difficult to reverse. Over-harvesting produces visible donor thinning, irregular extraction patterns and a depleted reserve for a second session that many patients will eventually need.
Where the requested coverage exceeds what the donor can responsibly supply, the honest answer is a staged plan or a revised expectation — not a larger session.
Specialised protocols
Some presentations cannot be treated with a standard workflow. Hairmedico maintains dedicated protocols where follicular anatomy, pattern of loss or surgical history changes the technique.
Curved follicles curve beneath the skin as well as above it. Extraction requires adapted punch selection, angulation and depth control to avoid transection, and placement must respect the natural curl direction. The favourable trade-off is coverage: high curl produces strong visual density from fewer grafts.
Female pattern loss is typically diffuse rather than zonal, and the donor area is often less stable. Assessment must exclude non-androgenetic causes first. Many cases are best served by unshaven or partial-shave techniques and density work between existing hair rather than a redrawn hairline.
Previous procedures leave constraints: a depleted donor area, scarring, misangled grafts or a hairline placed too low. Revision work is planned around what remains — often combining graft redistribution, scar camouflage and a corrected design, staged across more than one session.
The patient journey
The sequence below is fixed. Each stage produces a documented output that the next stage depends on, which is why the order matters.
Photographic assessment
Clear photographs of the front, sides, top, crown and donor area are reviewed by Dr Musbeh. This produces a preliminary opinion on candidacy, pattern classification and indicative graft range.
Medical consultation
Medical history, medication, previous procedures, family pattern and expectations are discussed. Where hair loss may not be androgenetic, further investigation is requested before any surgical date is offered.
Surgical plan and package selection
Zone-by-zone graft allocation, donor budget, technique and the level of surgeon involvement are confirmed in writing. Pricing follows the plan; the plan does not follow the price.
Arrival and pre-operative review
Blood analysis, direct clinical assessment and final confirmation of the design with the patient in front of a mirror. The hairline is agreed before anaesthesia, not during.
Surgery
Local anaesthesia, extraction, graft preservation, channel creation and placement, with breaks scheduled through the day. Duration depends on graft count and technique.
First wash and discharge instructions
The first wash is performed at the clinic and demonstrated to the patient. Written aftercare covering washing, sleeping position, medication, sun exposure and activity restriction is issued in the patient's own language.
Structured follow-up
Progress is reviewed against the expected growth curve at defined intervals. Where native hair continues to thin, medical treatment is adjusted rather than deferred to a second surgery.

What to expect
Hair transplantation follows a biological timetable that cannot be accelerated. Understanding it in advance prevents the most common source of patient anxiety: the shedding phase.
Crusting forms and resolves. Redness and mild swelling are common. Grafts secure in position during the first ten days.
Transplanted hairs shed. This is expected: the follicle remains and enters a resting phase. The scalp appears close to its pre-operative state.
Initial growth commonly begins. Emerging hairs are fine and may appear irregular in distribution.
Density builds and calibre thickens. Frontal zones typically mature ahead of the crown.
Most patients observe substantial development. Crown growth may take longer, and final texture can continue refining beyond twelve months.
International patients
Most Hairmedico patients travel from the United Kingdom, France, Germany, the Benelux countries, Switzerland and the Gulf. The clinical relationship begins before departure and continues long after the return flight.
Distance should not reduce the standard of follow-up. Reviews are scheduled at month 1, 3, 6, 9 and 12, conducted remotely with standardised photographs so that progress is compared against a consistent baseline rather than assessed from memory.
Where native hair loss continues — which it often does, since surgery does not treat androgenetic alopecia in untransplanted hair — the medical component of the plan is reviewed and adjusted at the same intervals.
A hair transplant is a single day. Managing hair loss is a decade.
For patients based in France and Luxembourg, consultation hubs in Paris and Luxembourg allow the initial assessment and later reviews to take place in person without travelling to Istanbul.

Frequently asked questions
Local anaesthesia significantly reduces discomfort during the procedure. Sensitivity and pain perception vary between patients, and mild postoperative discomfort can occur.
The anaesthetic injection itself is the most frequently reported discomfort. Beyond it, most patients describe the day as long rather than painful. Postoperative discomfort is usually managed with simple analgesia and resolves within the first few days.
Transplanted follicles are generally more resistant to androgenetic hair loss. However, untreated native hair may continue to thin, and long-term results depend on diagnosis, planning, donor quality and postoperative care.
This is why the surgical plan and the medical plan are prepared together. A transplant that ignores ongoing native loss can look excellent at twelve months and disappointing at five years — not because the grafts failed, but because the hair around them continued to recede.
The graft requirement cannot be determined from a universal number. It depends on the size of the treatment area, donor capacity, hair calibre, follicular density, hair-loss pattern and long-term treatment strategy.
Any figure quoted before donor-area analysis is an estimate for pricing purposes, not a clinical conclusion. Two patients with the same Norwood classification can require materially different graft counts because calibre and donor density differ.
Initial growth commonly begins around the third or fourth month. Most patients observe substantial development between 9 and 12 months. Crown growth may take longer.
Shedding of the transplanted hairs between weeks two and eight is expected and is not a sign of failure. The follicle remains in place and re-enters growth after a resting phase.
Not necessarily. Partial-shave and selected unshaven procedures may be possible depending on the technique, donor area and number of grafts required.
Unshaven procedures are more time-intensive and are typically limited in graft volume. Suitability is confirmed at assessment rather than promised in advance.
No technique is universally best for every patient. The appropriate method depends on the treatment area, existing hair, graft requirement, hair characteristics and surgical plan.
A clinic that presents one technique as superior in all circumstances is describing its own workflow, not your anatomy. In practice, methods are frequently combined within a single session.
It depends on the package selected, and it is stated explicitly before you commit. In the VIP package, Dr Arslan Musbeh personally performs graft extraction and channel creation. In the Gold package, he personally designs the hairline and performs channel creation, with the remaining stages completed by the medical team according to the surgical plan. In the Silver package, the procedure is carried out by the trained medical team under the clinic's established medical protocols and supervision.
In all three, diagnosis, surgical planning, hairline design, intraoperative supervision and postoperative review remain with the surgeon.
In most cases, yes — provided the donor area has been managed responsibly during the first session. This is one of the practical reasons Hairmedico does not maximise graft numbers on a first procedure.
A second session is usually scheduled no earlier than twelve months after the first, once the result of the initial procedure can be assessed accurately.
Patients can submit clear photographs of the front, sides, top, crown and donor area for an initial medical evaluation. A final plan is confirmed following direct clinical assessment.
Photographs should be taken in natural daylight, with dry hair, without styling product, and from a consistent distance. The clearer the input, the more accurate the preliminary opinion.
Next step
Send clear photographs of the front, sides, top, crown and donor area. Dr Musbeh reviews each submission personally and returns a preliminary opinion on candidacy, pattern and indicative graft range.
Istanbul · Paris · Luxembourg — assessment carries no obligation