Hair transplant for Norwood 3: the ideal graft count, technique, hairline design and results.
Norwood III is widely considered the most advantageous stage at which to address androgenetic alopecia surgically. The hair loss is visible enough to warrant treatment, the donor supply is typically maximal, the recipient zone is still limited enough for excellent density with a single session, and the patient's loss pattern is established enough for confident long-term planning. This guide explains everything specific to Norwood III hair transplant.
What Norwood III Looks Like
The Norwood III classification encompasses two presentations:
Norwood III (temporal): Deep temporal recession creating the classic M-shaped hairline. The mid-frontal hairline may still be intact, but the temples have receded significantly — creating an aged, receding appearance even at relatively young ages.
Norwood III Vertex: In addition to temporal recession, early crown thinning is present. The vertex begins to show through but has not yet merged with the frontal recession.
Both presentations are treatable in a single comprehensive session at Hairmedico, with excellent results at 12 months.
For an overview of all techniques available in a hair transplant procedure, understanding the approach before the consultation is valuable preparation.
Graft Count for Norwood III
| Norwood III Presentation | Graft range | Primary zones addressed |
|---|---|---|
| III — Temporal recession only | 1,500–2,200 | Temples + hairline restoration |
| III — Frontal + temporal | 2,000–2,800 | Full hairline + mid-scalp |
| III Vertex — frontal + early crown | 2,500–3,200 | Hairline + partial crown initiation |
The graft count for Norwood III is lower than for more advanced stages — and this is one of the reasons Norwood III results are often the most impressive. The recipient zone is smaller, enabling higher density with fewer grafts. A 2,000-graft session concentrated in a Norwood III recipient zone can achieve 45–55 FU/cm² — genuine cosmetic density that looks natural and full.
Why Norwood III Is the Optimal Surgical Timing
Donor supply at maximum: At Norwood III, the patient typically has their full lifetime donor supply available. No previous extractions have reduced it. The high-quality, high-density occipital and parietal donor zones provide excellent graft material.
Recipient zone manageable: The bald or thinning area is 60–90 cm² in most Norwood III presentations — a surface area that can be covered with excellent density in a single session without over-harvesting the donor.
Pattern established enough to plan: By Norwood III, the hair loss pattern has typically been stable for 1–2+ years. The frontal and temporal recession direction is clear. Planning a hairline that will age appropriately across the patient's loss trajectory is more straightforward than at Norwood II where the pattern may still be evolving.
Long-term planning window: A patient who addresses Norwood III at 32–38 has donor supply preserved for a second session at 45–50 if progression continues. This two-session lifetime plan is achievable at Norwood III; it is less achievable for patients who waited until Norwood V to have their first procedure.
Hairline Design at Norwood III
At Norwood III, the hairline design decision is the most consequential element of the entire procedure. The key considerations:
Age-appropriate positioning: A 30-year-old patient with Norwood III has the emotional motivation to want the lowest possible hairline for maximum youth effect. Dr. Arslan counsels every Norwood III patient on the 20-year view: a hairline designed for 30 may look appropriate at 35 but incongruous at 50 if native hair continues to recede around it. The optimal position is conservative enough to remain appropriate throughout the patient's life.
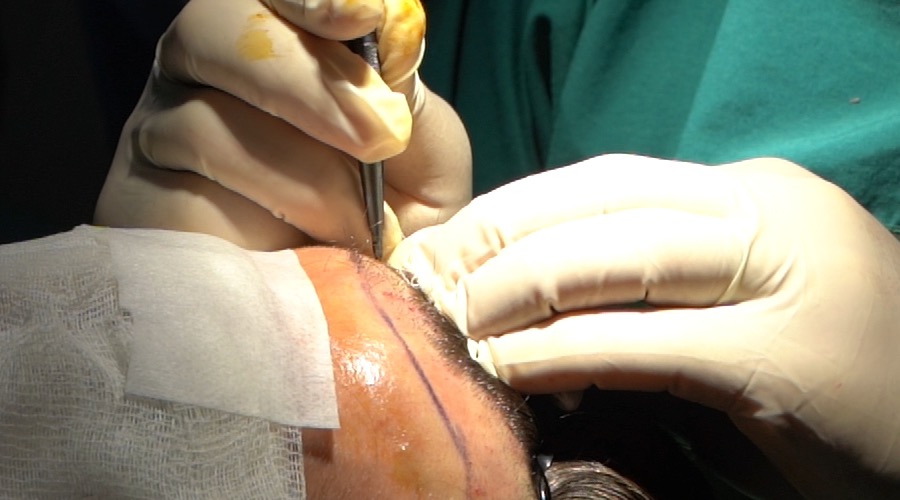
Temple restoration: Norwood III temporal recession typically warrants temple point restoration — the small extensions of hair at the temporal angles that dramatically change the framing of the face. Temple restoration requires fine single-hair grafts at very acute angles; Dr. Arslan personally places these grafts in the VIP package, and the technique follows his protocol in every case.
Frontal density gradient: The hairline edge must be created with single-hair grafts transitioning to 2-hair and 3-hair units — the natural density gradient that makes a hairline look undetectable. This micro-design decision is made graft by graft during the surgical phase.
More about Dr. Arslan's specific hairline design philosophy at Hairmedico About Us.
Norwood III Results at 12 Months
Norwood III is where the most satisfying single-session results are routinely produced. The combination of: limited recipient zone surface area, high donor density in the early stages, and the ability to achieve genuine cosmetic density in a single session produces outcomes that consistently exceed patient expectations.
At Hairmedico, Norwood III results at 12 months typically show: complete hairline restoration with natural gradation at the leading edge; temporal points restored or significantly improved; mid-scalp coverage with 40–50 FU/cm² density; and if vertex thinning was present, meaningful crown coverage that reduces the visible bald area significantly.
The result is natural enough that the large majority of Hairmedico Norwood III patients describe it as undetectable to people who did not know them before surgery. View all-inclusive package pricing at hairmedico.com/price.
